

Our Vision for a Smokeless World

I joined BAT as an R&D Management Trainee over 20 years ago. The company I joined then is fundamentally different from the one we are today.
Over the past decade in particular we have been on a clear journey, one defined by transformation, underpinned by science, and guided by a singular ambition: to reduce the health impact of our business and create A Better Tomorrow™ by Building a Smokeless World[3]. At the heart of this ambition lies Tobacco Harm Reduction (THR). First articulated by the U.S. Institute of Medicine, THR is based on a simple but powerful principle that adult smokers, who would otherwise continue to smoke, should have access to, and switch completely to, scientifically substantiated lower risk*† profile alternatives to cigarettes.
“I’m proud to present the 2026 edition of Omni™ – our dynamic, evidence-based manifesto for change and a leading authority on Tobacco Harm Reduction.”
Dr James Murphy
Director, Research & Science

Today, BAT is no longer simply evolving. We are leading. Whilst our transformation continues, we are changing at scale and powered by world-class science. Over more than 10 years, we have built one of the most comprehensive scientific programmes focused on THR, generating and publishing 288 studies in peer-reviewed journals to assess our Smokeless Products. This depth and breadth of evidence underpins the development of our three best-in-class, global Smokeless Product brands; glo (Heated Products), Vuse (Vapour Products), and Velo (Oral Nicotine Pouches).
These products operate without combustion, the primary source of the toxicants that cause smoking-related disease, and therefore significantly reduce users’ exposure to many toxicants as compared to cigarette smoking‡. Our scientific assessment, based on the weight of evidence, is that these Smokeless Products have the potential to present reduced risks*† relative to continued smoking.
Importantly, this is not theoretical. It is grounded in a growing body of laboratory, clinical, and real-world evidence, and in the lived experience of millions of adult consumers. Today, over 34 million adult consumers# have already chosen to use our Smokeless Products at least on a weekly basis, demonstrating both their acceptability and their potential to accelerate change at population level.
At the same time, the broader public health landscape is evolving. Smoking prevalence is declining across many regions of the world. According to the World Health Organization, the total number of tobacco users has fallen significantly over the past two decades. This progress is real and it should be accelerated.
The most significant barrier today to advancing THR adoption is no longer either a lack of innovation or a lack of evidence. Rather, it is a misunderstanding of evidence and, in some cases, the misinterpretation or selective use of science in policy discussions. Poor-quality and non-representative studies can disproportionately shape public discourse and regulation, creating confusion and undermining harm reduction opportunities. This matters. Because policy decisions taken today will determine how quickly smokers, who would otherwise continue to smoke, can transition away from cigarettes to smokeless alternatives.
We firmly believe that public policy should be grounded in the totality of robust, high-quality evidence and not isolated findings, outdated assumptions, or unreasonably precautionary approaches that fail to differentiate between combustible and Smokeless Products.
“While smoking prevalence continues to fall, progress is being held back by regulatory decisions too often shaped by selective or poor-quality science, undermining the full potential of evidence-based harm reduction.”
Dr James Murphy
Director, Research & Science
Sweden remains the most compelling example of what can be achieved. Sweden has the lowest lung cancer rates in the whole of the EU as a result of Sweden’s smoking prevalence rates being the lowest in the EU as adult smokers have transitioned to Smokeless Products, such as Oral Tobacco Products and Oral Nicotine Pouches[6]. It’s been reported that if Sweden’s mortality rates were applied to the rest of the EU, there would be 3.5 million fewer deaths over the next decade[6]; an outcome we believe public health authorities and regulators should seek.
The opportunity now is to replicate, and accelerate, this progress globally.
This is precisely why we launched Omni™. Omni™ is more than a publication. It is a platform designed to bring together the global evidence base on THR, combining our own research with independent science to support transparent and informed dialogue. We recognise that trust must be earned. That is why we are committed to:
- Advancing world-class, transparent science
- Engaging openly with regulators, public health experts, and the scientific community
- Supporting the development of evidence-based, proportionate regulation
Ultimately, progress will depend on collaboration. Tobacco Harm Reduction is not the responsibility of any one stakeholder, and it requires alignment across science, policy, and public health. Unfortunately, there remain few scientific forums where all stakeholders (industry included) can discuss scientific evidence and come to common conclusions on THR science to drive progress forward.
Public health messaging to smokers should mirror our view:
If you do not smoke, do not start. If you do, the safest option is to quit. If you wish to keep using nicotine, switch completely to a Smokeless Product.
After more than a decade of scientific investment, innovation and real-world evidence generation, we are clear in our conviction:
THR represents one of the most significant public health opportunities of our time.
Figure 1. Rank order of countries based on the Tobacco Control Scale and their smoking prevalence (%)
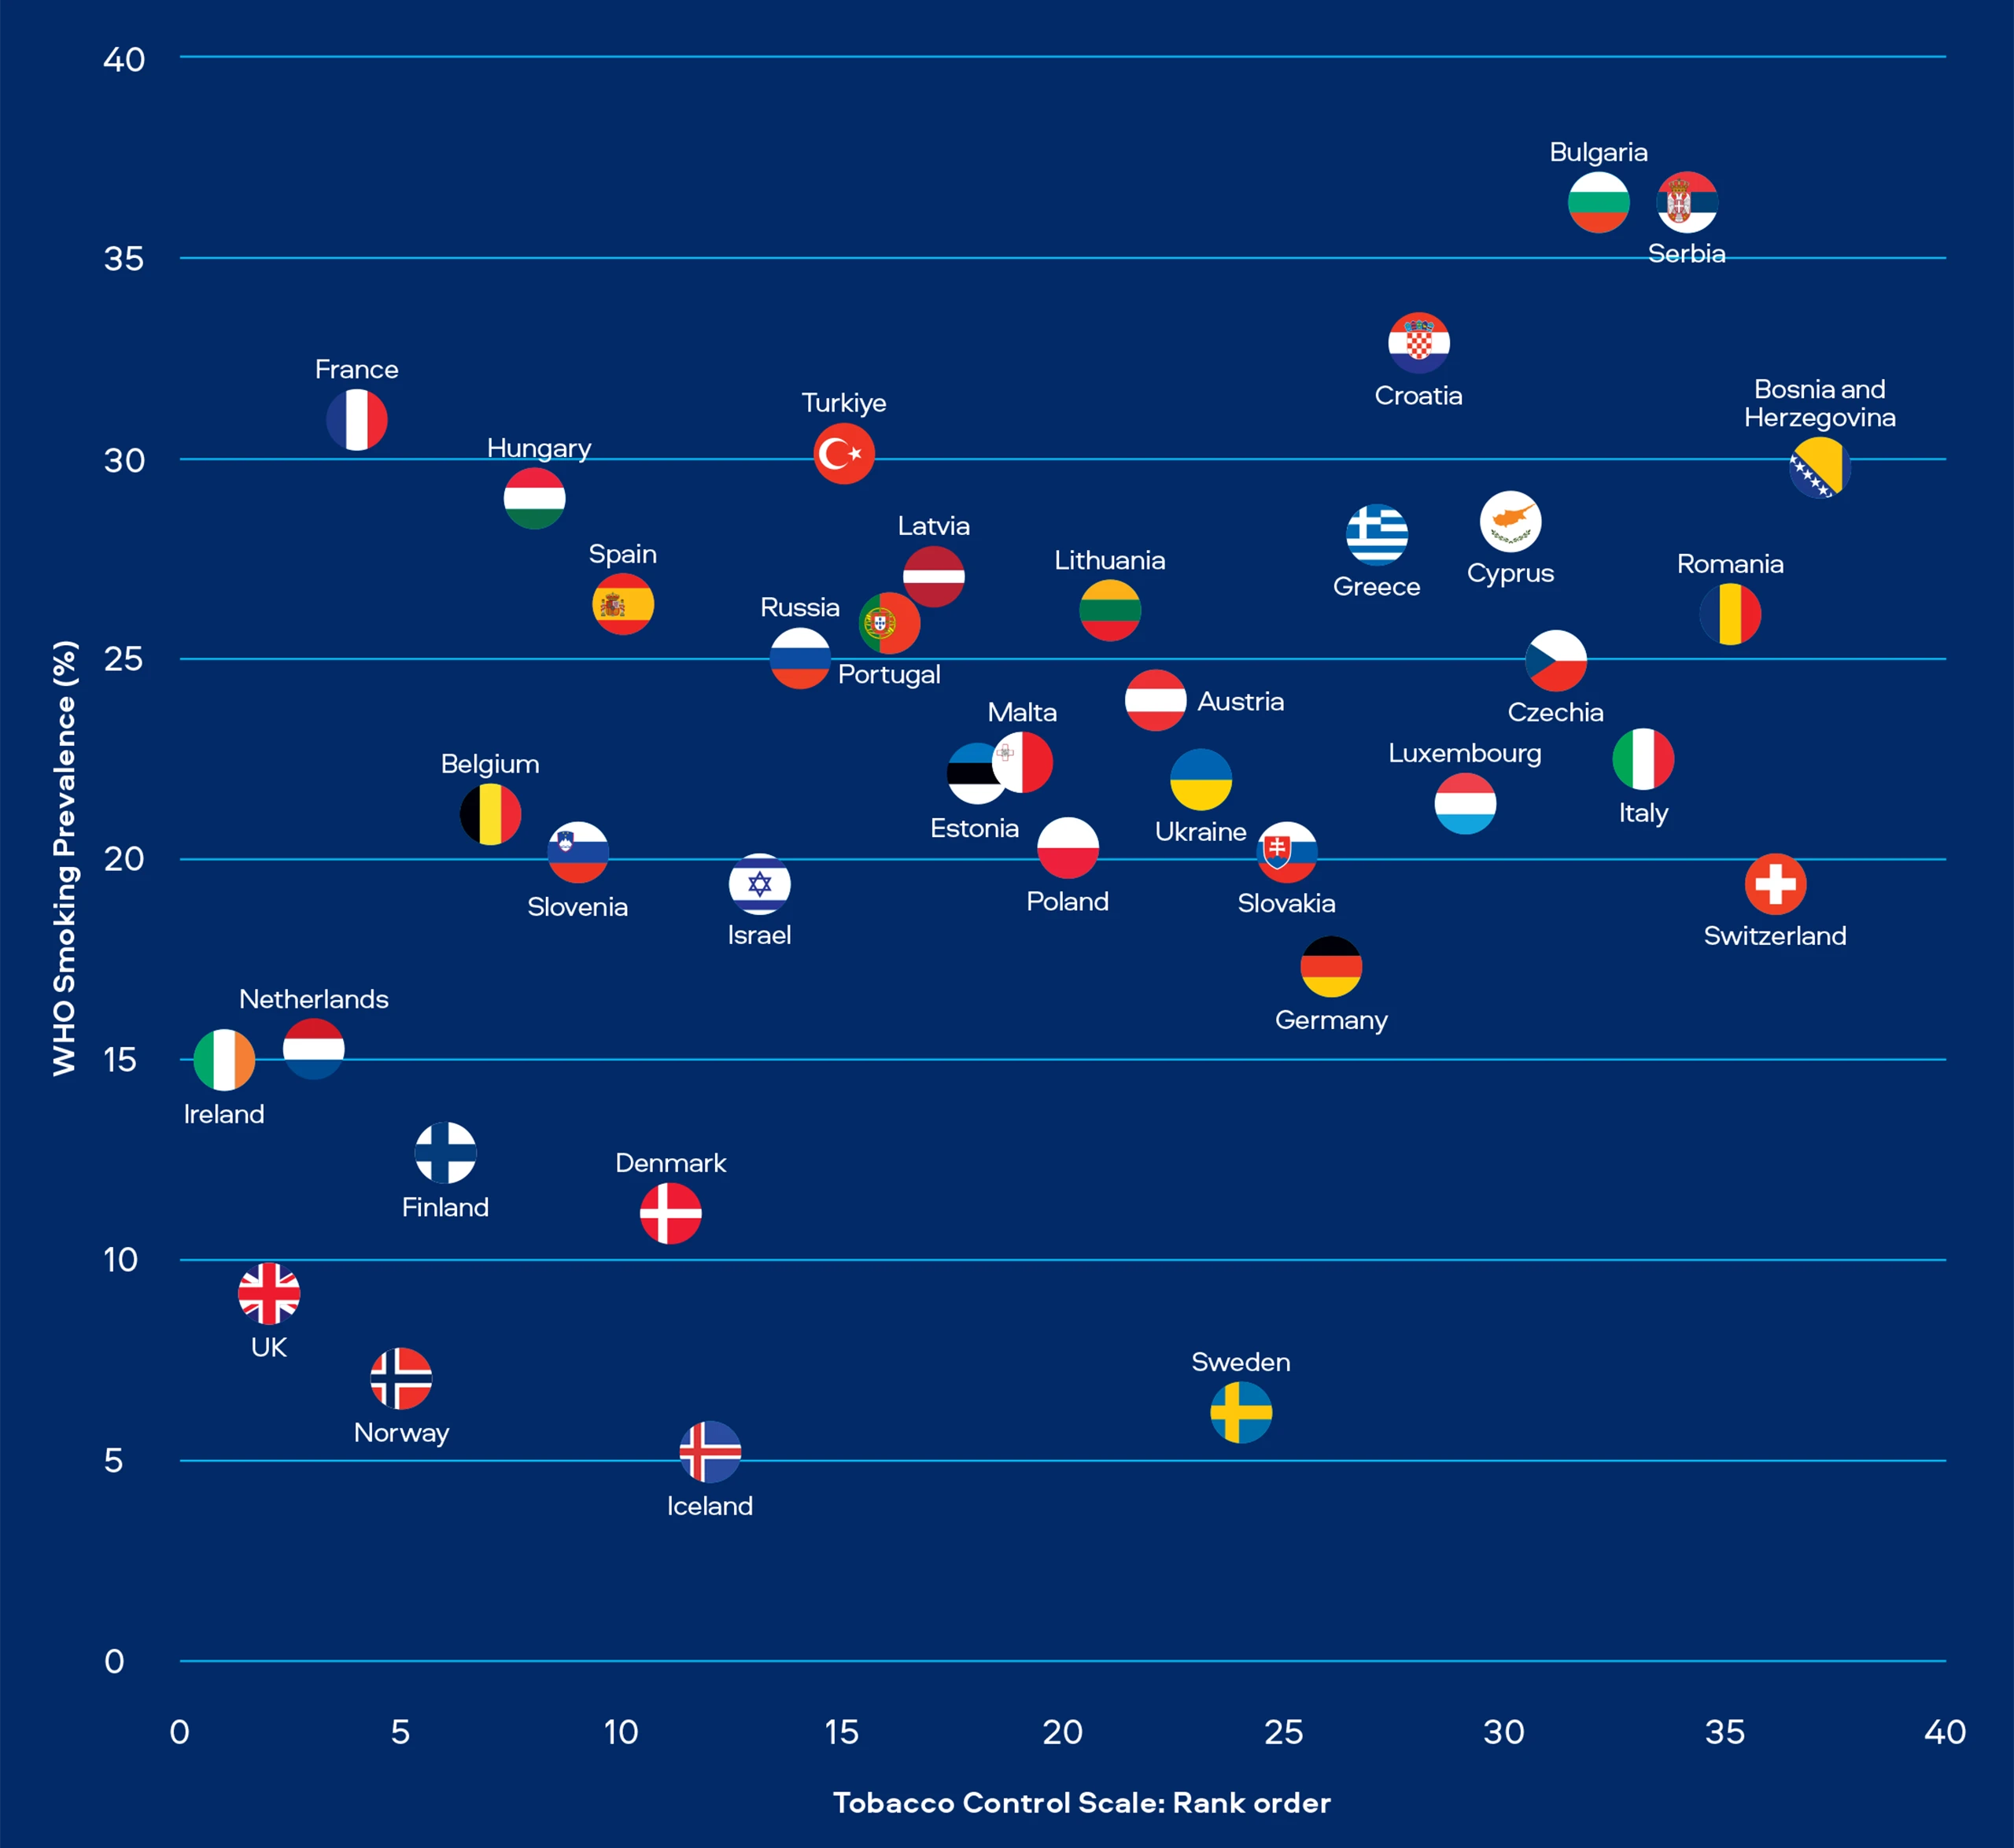
R2 = 0.21 (low correlation)
The R2 value calculated suggests that only 21% of a country's smoking prevalence can be attributed to their TCS score, ~80% is determined by other drivers.
The Tobacco Control Scale (TCS) is designed to assess policy implementation rather than public health outcomes. However, when TCS rankings are compared with smoking prevalence data reported by the World Health Organization (WHO), an apparent disconnect emerges[7].
Countries achieving relatively high rankings on the Tobacco Control Scale do not consistently exhibit the lowest smoking prevalence rates. Conversely, several countries that have achieved substantial reductions in smoking prevalence including some approaching the WHO’s long-term aspiration of reducing smoking rates to below 5%, receive comparatively lower rankings. Similarly, countries such as Greece and Croatia have reported significant reductions in smoking prevalence over recent years, yet their overall rankings do not fully reflect these outcomes.
Footnotes
* Based on the weight of evidence and assuming a complete switch from cigarette smoking. These products are not risk free and are addictive.
† Products sold in the U.S., including Vuse, Velo, Grizzly, Kodiak, and Camel Snus, are subject to FDA regulation and no reduced-risk claims will be made as to these products without agency clearance.
‡ Comparison with smoke from a scientific standard reference cigarette (approximately 9mg of tar) in terms of the average of the nine harmful components the World Health Organization recommends to reduce in cigarette smoke.
# Adult smokers are adult consumers who smoke daily. Adult smokeless product consumers are adult consumers who use any smokeless product category at least on a weekly basis. BAT smokeless product consumers are defined as adults who consume Vapour, Heating Products, Modern Oral pouches or Traditional Oral pouches at least on a weekly basis. For cross-manufacturer estimates, the smokeless products category excludes Traditional Oral pouches. For full definitions, please refer to the cautionary statement.
^ While we are aware of some evidence suggesting that dual use of cigarettes with Smokeless Products can, for some smokers, function as a step towards completely switching, we are clear that smokers should not delay making a complete switch or quitting smoking completely.
References
A full list of references for this page can be found in the section 11. References.

Exclusive access to the Omni™ Newsletter
Join the conversation shaping A Better Tomorrow™. Sign up to receive exclusive access to the Omni™ Newsletter and future Omni™ updates.
Signing up to the Omni™ Newsletter does not constitute consent to receive marketing communications.